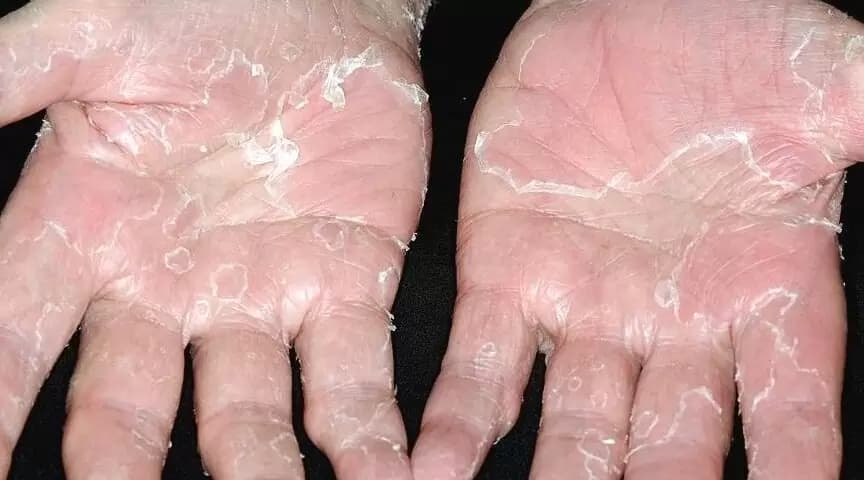
What is peeling skin syndrome?
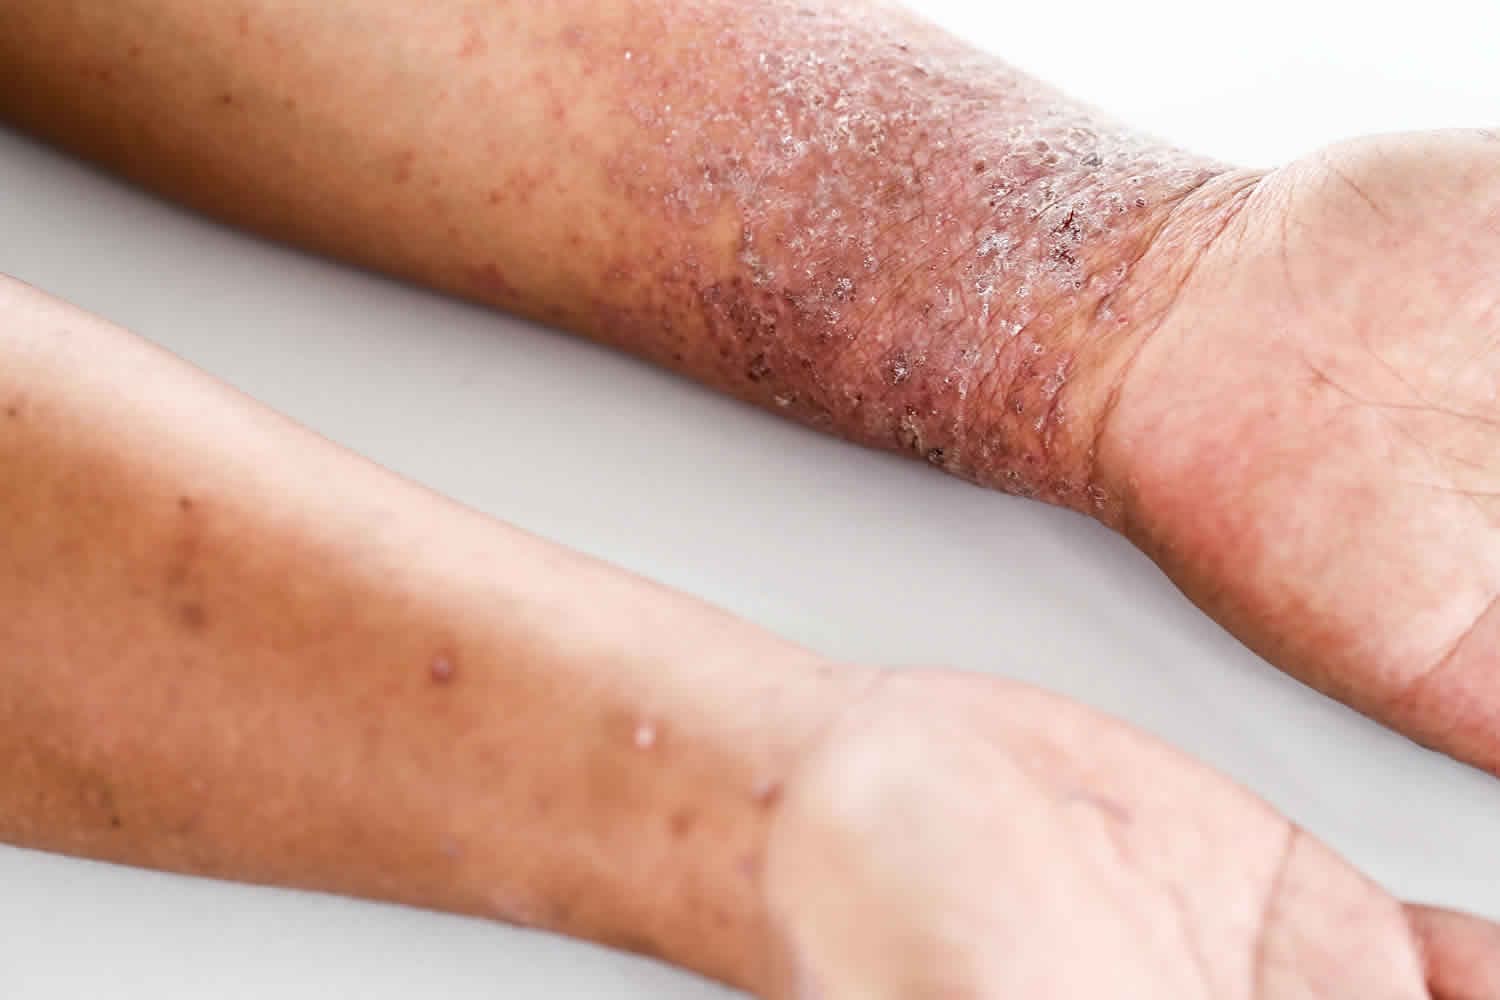
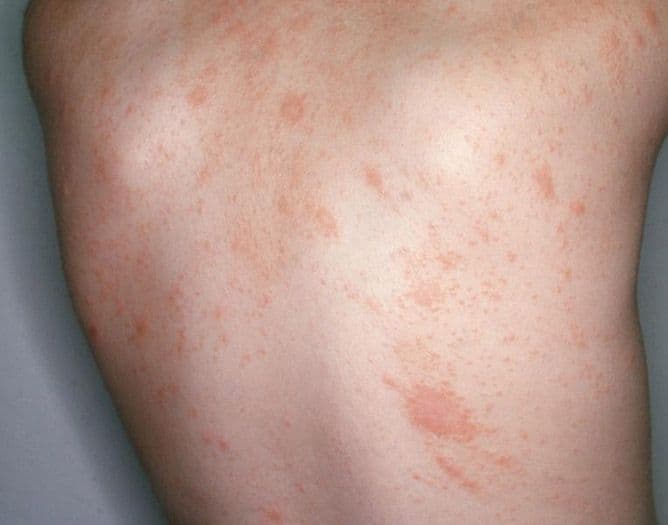
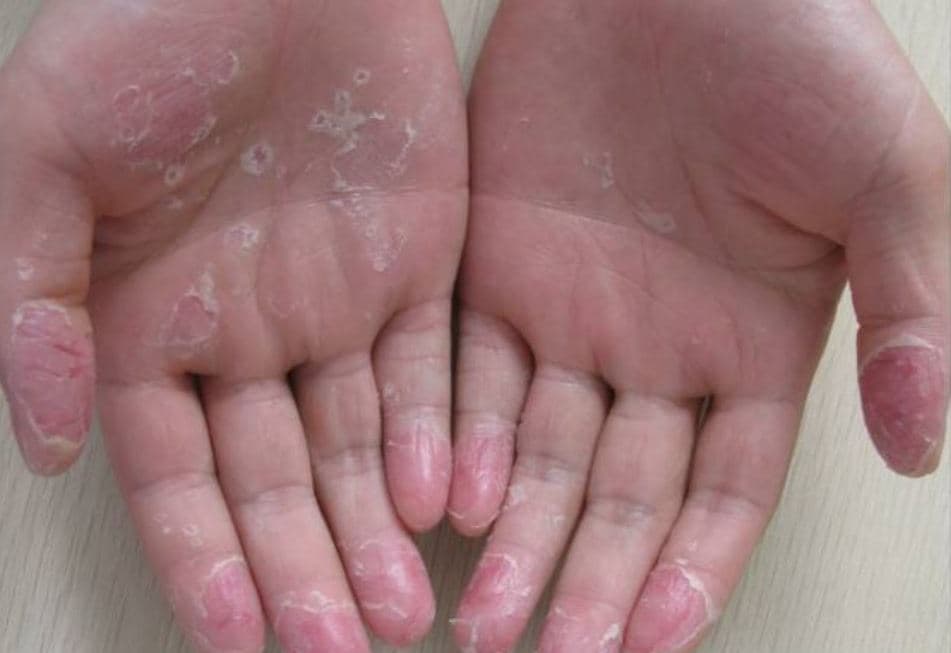
Peeling skin syndrome (PSS) is a group of rare inherited skin disorders in which the normal, invisible shedding of the outermost skin layer is speeded up and exaggerated. The result is painless, continual, spontaneous peeling of the top layer of the epidermis (the stratum corneum) from the layers beneath it (NORD). People with the condition, or their parents, can often lift off sheets of skin by hand, much as skin peels after a bad sunburn (NORD).
- It is classed among the congenital ichthyoses and the skin fragility disorders (NORD).
- Most forms appear at birth or in infancy, and the peeling may persist for life, with gradual improvement over time (NORD).
- It is not contagious: the peeling comes from the genes a person is born with, not from an infection (NORD, MedlinePlus Genetics).
- More than 100 cases have been described in the medical literature, in people of many backgrounds; because the features are often mild, the condition is probably underdiagnosed and underreported (NORD).
- Males and females are affected in equal numbers (NORD).
- Other names include deciduous skin, familial continuous skin peeling, skin peeling syndrome and exfoliative ichthyosis (NORD).
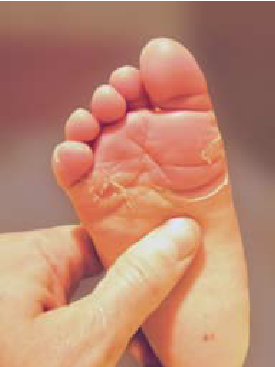
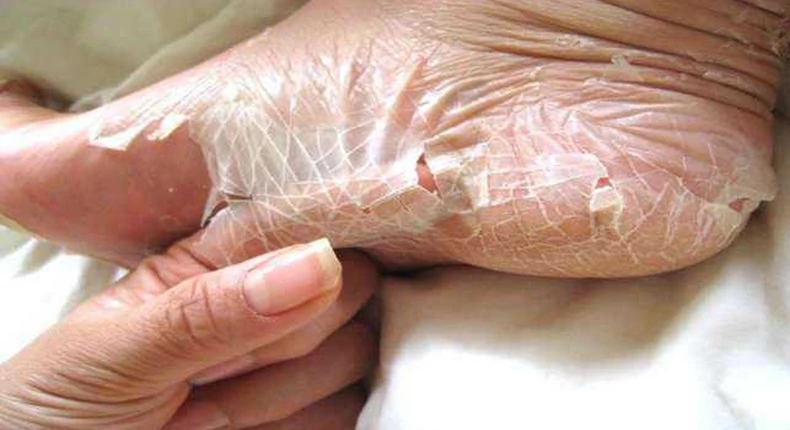
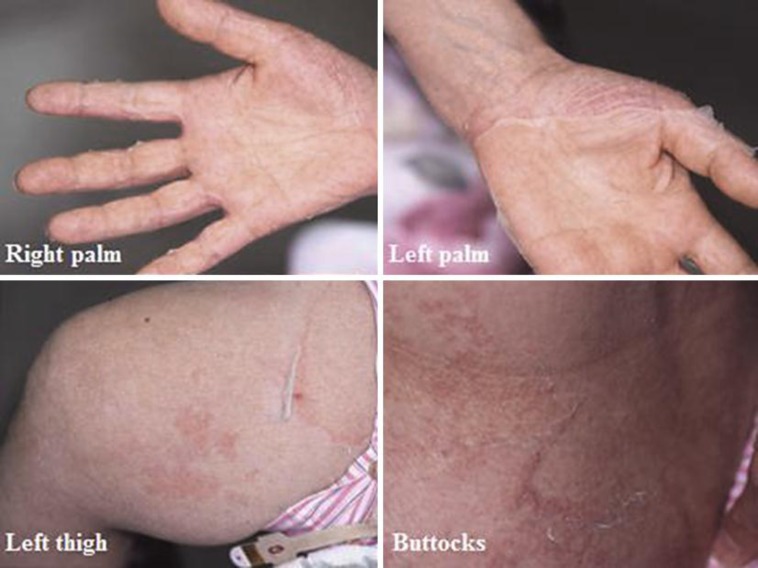
Peeling skin: is it the syndrome, or something more common?
Most people whose skin is peeling do not have peeling skin syndrome. The syndrome is rare (NORD), while peeling and flaking skin are common and usually have an everyday cause: sunburn, dry skin, eczema, psoriasis or a fungal infection (NHS, MedlinePlus). Two clues point towards the syndrome: peeling that started at birth or in infancy and has never fully stopped, and peeling that is painless and spontaneous rather than following a rash, an injury or an illness (NORD, MedlinePlus Genetics).
| Cause of peeling skin | How it differs from peeling skin syndrome |
|---|---|
| Sunburn | The skin is hot and sore first and flakes or peels a few days later; it usually gets better within 7 days. Do not scratch or try to remove the peeling skin (NHS). |
| Keratolysis exfoliativa (focal palmar peeling) | Common, mostly in young active adults. Small air-filled blisters on the fingers or palms burst and leave expanding rings of scale; it is not usually itchy, is worse in summer and often recurs within weeks. No genetic abnormality has been found, which separates it from the acral form of the syndrome (DermNet, NORD). |
| Athlete's foot (tinea pedis) | Itchy white patches between the toes, sore flaky patches and cracked skin, caused by a fungus and treated with antifungal creams, sprays or powders from a pharmacy (NHS). |
| Tinea manuum (fungal infection of the hand) | A slowly extending area of peeling, dryness and mild itching, usually on the palm of one hand, often with both feet affected as well. Skin scrapings confirm the fungus (DermNet). |
| Dyshidrotic eczema (pompholyx) | An itchy form of eczema with small fluid-filled blisters on the fingers and palms (DermNet). |
| Atopic eczema | Itchy, dry, cracked, scaly or thickened skin that flares and settles, typically on the elbows, knees and hands, usually starting in babies and young children (NHS). |
| Contact dermatitis | Itchy, blistered, dry and cracked skin that appears within hours or days of contact with an irritant or an allergen, most often on the hands and face (NHS). |
| Psoriasis | Dry, itchy, sore, flaky patches with silvery-white scale, usually 1 to 2 cm across, on the scalp, elbows, knees, trunk and lower back (NHS). |
| Ichthyosis vulgaris | The most common inherited ichthyosis (about 1 in 250 people): persistently dry skin with fine white scale that appears after about 2 months of age, sparing the skin creases (DermNet); the skin flakes rather than peeling in sheets. |
| Juvenile plantar dermatosis | A common dry-skin condition of children aged about 3 to 14: itchy or sore, shiny, glazed red skin with cracking and scaling on the weight-bearing parts of both soles, caused by friction and sweating in enclosed shoes; the toe webs and instep are usually spared, which separates it from athlete's foot (DermNet). |
| Scarlet fever | A sandpaper-like rash with a high temperature and a sore throat; the skin sometimes peels like sunburn as the rash fades. It needs antibiotics from a GP (NHS). |
| Staphylococcal scalded skin syndrome | Mostly children under 5. Fever and irritability are followed within 24 to 48 hours by a painful red rash and large fragile blisters; the top layer then peels off in sheets. It is treated in hospital (DermNet). |
| Stevens-Johnson syndrome | Flu-like symptoms, then circular patches darker in the middle, blisters and skin that peels very easily, with sores in the mouth, eyes or genitals. It is usually a reaction to a medicine and is an emergency (NHS). |
| Toxic shock syndrome | A high temperature, a rash that feels like sandpaper and flu-like symptoms; large areas of peeling skin are among the signs that need an emergency call (NHS). |
| Erythroderma | Redness over 90% or more of the skin, with scaling in fine flakes or large sheets 2 to 6 days later. It usually arises from an existing skin disease such as eczema or psoriasis, or from a drug reaction, and needs urgent medical care (DermNet). |
What causes peeling skin syndrome?
Healthy skin renews itself constantly. The cells of the top layer are held together by protein junctions, and enzymes break those junctions down at the right moment so that old cells can fall away unseen (NORD). In peeling skin syndrome, a change in one of several genes upsets this balance. Most of the affected genes code either for structural proteins of the surface cells, which make the cells tough and hold them together, or for inhibitors of the skin enzymes that control shedding (NORD); one codes for an enzyme that builds the cells' tough outer envelope (MedlinePlus Genetics). When a junction is weak or an enzyme is no longer held in check, the top layer separates too early and comes away in visible sheets (NORD).
The localised (acral) form is most often caused by changes in the TGM5 gene; a rarer acral form is linked to the CSTA gene (NORD). TGM5 makes transglutaminase 5, an enzyme needed to build the tough envelope around each surface cell. Without enough of it the envelope is weak, and the outermost cells separate easily from the skin beneath. The peeling is most noticeable on the hands and feet because those areas are exposed to the most moisture and friction (MedlinePlus Genetics). One particular TGM5 variant is widespread across Europe and has been found in both gene copies in people in the general population who were never diagnosed, so the acral form is probably more common than the number of diagnosed cases suggests (NORD).
The inflammatory type involves genes such as CDSN and DSG1; the related Netherton syndrome is caused by changes in SPINK5, where the loss of an enzyme inhibitor leads to excessive shedding and a severely leaky skin barrier (NORD).
How it is inherited
All known forms of peeling skin syndrome are inherited in an autosomal recessive pattern: a child is affected only when they inherit a changed copy of the gene from each parent. The parents are carriers and usually have no symptoms (NORD, MedlinePlus Genetics). When both parents are carriers, each pregnancy carries a 25% chance of an affected child, a 50% chance of a child who is a carrier like the parents and a 25% chance of a child who inherits two normal copies. The risk is the same for boys and girls. Parents who are blood relatives have a higher chance of carrying the same changed gene (NORD).
Symptoms of peeling skin syndrome
The defining feature is peeling that is spontaneous, painless and continual (NORD). Other features depend on the form of the condition (NORD, MedlinePlus Genetics):
- Sheets of skin can often be removed by hand, as after a severe sunburn (NORD).
- The skin underneath may be temporarily red and itchy, and it heals without scarring (MedlinePlus Genetics).
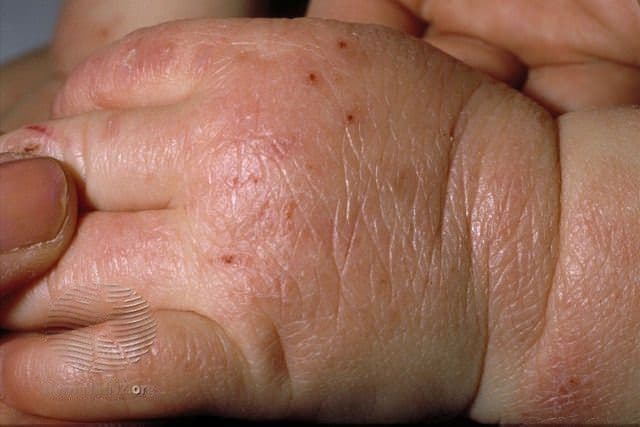
- Some forms cause blistering and skin fragility, with blisters and erosions on the hands and feet at birth or during infancy in the localised types (NORD).
- Some people also have itching, short stature and new hairs that pull out more easily than normal (NORD).
- The inflammatory types can add widespread red, scaly skin (erythroderma) or thickened red plaques, raised levels of the allergy antibody IgE, allergies, a tendency to infections and poor growth (NORD).
What makes the peeling worse: friction and other mechanical irritation of the skin, heat, sweating, humidity and contact with water (NORD, MedlinePlus Genetics).
Types of peeling skin syndrome
Doctors group the condition by how much skin is involved and whether the skin is inflamed (NORD).
| Form | Where the skin peels | Other features | Course |
|---|---|---|---|
| Localised (acral) type: PSS2 (TGM5) and PSS4 (CSTA) | Palms, soles and the backs of the hands and feet, occasionally the arms and legs | Superficial blisters and erosions from birth or infancy; can resemble epidermolysis bullosa simplex, another blistering skin disorder. The CSTA form adds dry scaly skin and excessive sweating (NORD, MedlinePlus Genetics) | Mild; in the TGM5 form not associated with other health problems, and the skin heals without scarring (MedlinePlus Genetics) |
| Generalised non-inflammatory type: PSS3, PSS5, PSS6 (FLG2, SERPINB8 and others) | The whole body | Generalised dryness and peeling without marked redness; blisters are rare (NORD) | Typically improves with age, but is triggered or aggravated by heat and mechanical trauma (NORD) |
| Generalised inflammatory type: PSS1 (CDSN) and SAM syndrome (DSG1); features of this type also occur in Netherton syndrome (SPINK5) | The whole body | Widespread redness or thickened red plaques, raised IgE, allergies, susceptibility to infections and failure to thrive or metabolic wasting (NORD) | The most severe type; can be life-threatening, especially in the newborn period (NORD) |
| PLACK syndrome (CAST) | The whole body | Peeling together with white nails, small callus-like thickenings on the palms and soles and over the knuckles, and inflammation at the corners of the mouth (NORD) | Starts in infancy and improves over time, although it may worsen with heat in summer (NORD) |
Netherton syndrome is a closely related congenital ichthyosis in which the features of the inflammatory type can be present (NORD). It combines inflamed, red, scaly skin from birth or the first weeks of life, short brittle "bamboo" hair and a strong tendency to allergies. Because the skin barrier is leaky, a newborn loses heat, water and protein through the skin and is at risk of infections that can be life-threatening. Many infants fail to thrive in the first year; from the second year most children start to improve, although about half remain underweight and short (DermNet).
When to see a doctor
Ask a dermatologist to assess the skin if you notice (NORD, MedlinePlus Genetics):
- persistent, unexplained peeling that does not settle with regular emollients;
- peeling that began in infancy and has never completely stopped;
- similar peeling in other family members;
- peeling over the whole body, or peeling that is intense;
- blisters or raw patches on an infant's hands and feet (NORD);
- a child whose peeling comes with poor growth, repeated infections or allergies (NORD, DermNet).
Same-day care: a newborn whose skin is widely red, scaly and peeling needs to be seen in hospital the same day, because the leaky skin loses heat, fluid and protein and infection can be life-threatening (DermNet).
Call 999 (UK and Ireland) or 112 (elsewhere in Europe), or go to the emergency department (A&E), if a rash with blistering or peeling skin appears after an infection or a new medicine, especially with sores in the mouth, eyes or genitals, wheezing or difficulty breathing (NHS, Stevens-Johnson syndrome), or if large areas of skin are peeling together with a high temperature, a sandpaper-like rash, confusion or fast breathing (NHS, toxic shock syndrome). A young child with a high temperature and a painful red rash that blisters and peels in sheets within a day or two may have staphylococcal scalded skin syndrome, which needs emergency assessment and hospital treatment (DermNet).
How peeling skin syndrome is diagnosed
A detailed history and an examination of the skin are often enough to make the diagnosis; at times a small sample of skin (a biopsy) is examined under the microscope (NORD). The doctor will want to know when the peeling started, what the skin looked like at birth, which parts of the body are involved, whether anyone else in the family is affected and whether there are other features such as eczema, abnormal hair or nails (DermNet).
The continual shedding of large sheets of skin is what distinguishes peeling skin syndrome from Netherton syndrome and from the other recessive congenital ichthyoses, in which the skin scales persistently rather than peeling repeatedly: the shiny membrane of a so-called collodion baby, for example, peels off after a few weeks and does not come back, whereas in peeling skin syndrome the peeling returns time after time (NORD). Genetic testing can identify the gene involved and confirm the form, which matters for counselling the family (NORD, MedlinePlus Genetics). In an inflammatory form the doctor also looks at hair shafts under the microscope for the bamboo-hair change of Netherton syndrome and checks blood IgE levels and signs of infection (DermNet, NORD).
When only the palms and soles peel, the more likely diagnosis is keratolysis exfoliativa or another common cause rather than the syndrome: in keratolysis exfoliativa skin scrapings for fungus and patch tests for contact allergy are negative, the peeling starts with air-filled blisters and recurs in episodes, and no gene change has been identified (DermNet, NORD).
Treatment and skin care
There is no treatment that corrects the gene change. Care aims to reduce the peeling, protect the skin and prevent infections (NORD, DermNet).
- Emollients are the foundation. Skin-softening ointments, applied especially after a bath while the skin is still moist, can offer relief; plain petroleum jelly is preferred (NORD). Emollients work best on damp skin: apply them as soon as you have patted the skin dry after washing, and use them at least 3 or 4 times a day, smoothing rather than rubbing them in (NHS). Ointments suit very dry, thickened skin and night-time use; creams are less greasy for the daytime (NHS).
- Wash gently. Use a leave-on emollient or an emollient soap substitute instead of soap, shampoo and shower gel, which dry the skin (NHS). A short lukewarm shower is better than a long hot bath (DermNet).
- Humectant creams can sting. Emollients containing urea or lactic acid hold water in the skin and have a mild descaling effect, but they often sting on scratched or cracked skin (DermNet), so a plainer product is better on those areas; the same applies to wash products that sting and do not settle (NHS).
- Avoid the triggers. Overheating, heavy sweating, long contact with water and friction are the main aggravating factors (NORD, MedlinePlus Genetics). Loose, breathable cotton clothing, a cool room and short baths all help; a humidifier is useful in winter when heated indoor air dries the skin (DermNet).
- Protect freshly peeled skin. The skin underneath is red and itchy for a time (MedlinePlus Genetics). Treat it as you would sunburnt skin: keep it covered from direct sun until it has healed and do not pull at skin that is still attached (NHS).
- Do not borrow eczema or ichthyosis treatments. Neither the steroid creams used for eczema nor the oral vitamin A derivatives used for some ichthyoses are indicated or effective in peeling skin syndrome, and both can cause serious side effects (NORD). If the peeling is accompanied by eczema-like inflammation, a dermatologist decides what is appropriate.
- Treat infections promptly. Skin whose barrier is damaged is at risk of infection; in Netherton syndrome antibiotics are used for skin infections, and preventing infection is one of the goals of care (DermNet).
- Fire safety. Emollients that contain paraffin soak into clothing and bedding and make them catch fire more easily: do not smoke or go near naked flames when using them (NHS).
Inflammatory forms are managed differently. A newborn with Netherton or SAM syndrome needs hospital care, because the condition can be life-threatening at that age (NORD, DermNet); the child is then followed by a dermatologist and, as needed, a paediatrician and an allergist. There is no specific treatment, so the goals are to keep the skin moisturised, prevent and treat infections, manage allergies and watch growth (DermNet, NORD). In Netherton syndrome, steroid creams may help older children with eczema, but in infants with widespread red skin too much is absorbed, so they are used only under specialist direction (DermNet).
Genetic counselling is recommended for affected people and their families to discuss the risk of having children with the disorder and the possibility of genetic testing (NORD).
Living with peeling skin syndrome
- Clothing: soft, breathable natural fabrics such as cotton, with as few rubbing seams as possible, because friction brings on peeling (NORD).
- Home: a cool bedroom and a humidifier in the heating season; drink enough water, which matters for dry skin (DermNet).
- Sport and swimming: choose activities with little friction; shower briefly in lukewarm water afterwards and apply emollient straight away, because sweat and water aggravate the peeling (NORD, MedlinePlus Genetics).
- Nursery and school: explain that the condition is not contagious (NORD) and that the child only needs to reapply emollient more often than their classmates; most activities can continue with extra emollient and clothing that limits friction.
- Emotional support: visible peeling can make teenagers avoid sport, swimming or social situations; talking to a psychologist is a reasonable part of care in that situation.
- Follow-up: regular reviews with a dermatologist, and in the inflammatory forms with the wider team, to adjust skin care, monitor growth and manage allergies (DermNet).
Outlook
Peeling skin syndrome is a long-term condition, but the peeling may lessen gradually with age (NORD). The acral form is mild: it is not associated with any other health problems, the peeling is painless and the skin heals without scarring (MedlinePlus Genetics). The generalised non-inflammatory form also typically improves with age (NORD). The inflammatory forms vary widely; the newborn period is the most dangerous time, and in Netherton syndrome most children begin to improve from the second year of life, although about half remain short and underweight; later there are often periods with little or no disease activity (DermNet).
Online dermatologist consultation
If your skin or your child's skin peels continually and emollients alone are not enough, you can book an online consultation with an iDerma dermatologist. Send clear photographs of the peeling areas and describe when it started, what makes it worse and whether anyone in the family has similar skin. The dermatologist will assess whether the picture looks like peeling skin syndrome or like one of the far more common causes of peeling, and will say which tests are needed. A skin biopsy or genetic test, where required, is arranged in person with a dermatologist or a genetics service near you.
What to do now
- Start applying an emollient after every wash and several times a day, and cut out hot water, heavy sweating and friction: this reduces peeling in the syndrome and in the common dry-skin causes of peeling (NORD, NHS, DermNet); it does not treat an infection or a drug reaction.
- If the peeling began in infancy, keeps coming back or runs in the family, book a dermatology assessment; the diagnosis is confirmed by examination, and where needed by a biopsy and a genetic test (NORD).
- A newborn with widespread red, peeling skin must be seen in hospital the same day (DermNet), and an infant with blisters on the hands and feet should be seen soon (NORD).